News & Views on Systemic Body Odor and Halitosis such as trimethylaminuria TMAU. If you have fecal odors or bowel odors it may be metabolic/systemic

Showing posts with label fecal body odor. Show all posts

23 June 2018

someday : 'fecal body odor' debate in Parliament ?

Someday politicians could be having a debate about 'fecal body odor' 'metabolic body odor' 'systemic body odor' 'TMAU' in their parliament / senate / congress etc.

Recently a 'M.E.' debate was held in the UK Parliament.

Here is the UK 'request for debate' stage (to show the interest of the MPs of all parties)


Someday they could be talking about (choose your label) :
FECAL BODY ODOR
METABOLIC / SYSTEMIC BODY ODOR
MET-BO
TMAU
etc

It shows that politicians are very aware of M.E. and realise it is ignored.
Perhaps the same politicians who have sympathy with ME would be sympathetic to FBO.

What can be done ?
One could write their local politician about FBO etc.
e.g. MP, Senator, Rep, UK, USA, Canada, anywhere.

Also could look for politicians sympathetic to M.E. etc and write them.

Health systems and researchers are not interested in FBO/TMAU etc.
They need to be forced by politicians to act.

In UK
MPs make All Party Parliamentary Groups.
M.E. seems to have a group (2016) ME APPG

Full video :
Recent UK Parliament M.E. debate (in backroom, not main chamber)


Other awareness ideas :
Bus ad
Write to high profile 'TV Dr's/naturopaths'


Get new posts by email

12 June 2018

FMO3 survey to understand patterns in community

I would suggest its better to do the FMO3 DNA test first rather than the Urine test.
It's important we see a pattern of FMO3 variants to use as proof and to understand.

The FMO3 coding part is a 532 amino acid sequence (3 x 532 nucleotides)

Ways to FMO3 DNA test :
Full sequencing (hard to access)
23andme (23 of the 532 codons)
Geneology dna tests (raw data ... about 25 codons ?)

Ethnicities often have 'haplotypes', certain groups of variants.

Below is an 'ad-hoc' quick FMO3 survey.
The results will be made public.
Intention is to look for patterns.

Link for the survey (e.g. to share) https://tinyurl.com/y7kyxzpc


Problems with DNA testing :
If via a Health system lab, they don't give the 532 data, but rather mention variants they think important. They are likely very conservative.
If via 23andme : You need to look in the raw data. Not too hard. E.g. search FMO3. 

Why FMO3 ?
FMO3 oxidizes 1,000s of substrates, that are sulfides. amines, or phosphate containing.
It is my current opinion that FMO3 weakness is the cause of most cases of 'fecal body odor'.
Most enzymes have only maybe 1 to 10 substrates to alter.
But the oxidizer group, which includes FMO3, have 1,000s of substrates to alter. 


Get new posts by email

25 March 2018

Potential 2 year FMO3 Study

A Metabolic Consultant has offered to do a 2 year study on 2 ways to improve FMO3 function.

Part 2 (part 1 in the paper). would focus on NONSENSE mutations, which are rare but usually severe.
Part 1 would focus on MISSENSE mutations, which will be the vast majority of TMAU1 cases.
Speculation suggests that TMAU2 cases could also possibly be mild missense cases.

I make MISSENSE part 1 as this will be the vast majority
e.g. E158K E308G etc

What's needed for the study to happen :
A TRUSTED PARTY to set up a CROWDFUNDING PAGE.
Youcaring is suggested as it's free and has few clauses : Youcaring
But any crowdfund site would do.

Study cost : about $US 100,000

Why ? 
Someone will be hired fulltime for 2 years.
Plus equipment etc

Study basics :
1. Using ATALUREN to see if it helps with NONSENSE mutations.
2. DRUG REPURPOSING : going through many drugs in FMO3 cells to see if any improve FMO3 function. This would help with MISSENSE mutations.

Drug Repurposing often happens in pharma-world.
Such as viagra originally being for heart disease.
Often multi-uses are found for drugs accidentally.

The study needs funding

A best option would seem to be crowdfunding.
possible scenarios :
A trusted individual or collective to take on the crowdfund.
e.g. A group of respected older women ?
or
Using the REACT Fund as a trusted proxy (if they let the consultant have the money)
RE(ACT) TMAU FUND
or
Any other ideas

Fuller outline of the potential study

 Time-lines for the project (at half-yearly milestones):


Study component
Year 1
Year 2
Generation of a range of FMO3 nonsense and missense mutations and the in vitro tools for their functional analysis in a cell culture system
X
X


Evaluation of the efficacy of read-through agents and other drugs in our in vitro cell culture system, including acquisition of structural and functional evidence


X
X

2.  Repurposing of existing drugs:

TMAU is caused by a functional deficiency of the FMO3 protein.  Many of the missense mutations of the FMO3 gene are hypomorphs, ie there is some residual activity of the enzyme, albeit not enough to prevent the accumulation of TMA.  Augmenting expression of the faulty gene through activation of the FMO3 promoter, could improve overall FMO3 enzyme expression, with significant amelioration of the disorder(19).  Libraries of known therapeutic agents are commercially available that can be used in high throughput screening assays to screen for possible opportunities to “repurpose” the drug, ie apply it in a therapeutic context for which it was not originally designed.

We propose to use the cell culture models developed by us in a high throughput screening approach to identify new potential therapeutic agents that could augment expression of the FMO3 gene.

If we demonstrate potential in vitro efficacy of specific well-established therapeutic agents, we will then potentially be in a position to move to clinical trials in patients with trimethylaminuria, particularly if the therapeutic agent identified has an existing therapeutic track record in other disorders.

1.  Read through of premature termination mutations: (Nonsense mutations)

Premature termination or nonsense mutations arise as a result of a single nucleotide change in a gene where the change leads to the conversion of an amino acid in the protein sequence to a premature stop codon.  Such mutations often result in the protein losing most if not all of its functional capacity.  It was recognised a number of years ago that aminoglycoside antibiotics can force the transcriptional machinery to read through the premature stop mutations, and allow the normal protein to be made, restoring activity of the protein(13).  However, aminoglycoside antibiotics have significant side effects and are not a viable therapeutic option.  More recently a new class of drugs has been developed that has the capacity to promote read through of premature termination mutations, and which appear to be totally non-toxic(14).  One in particular, PTC124, has been shown to result in the production of normal dystrophin in the mdx mouse model of Duchenne muscular dystrophy(14), and has been used in clinical trials in human subjects with cystic fibrosis, with clear benefits being found(15).  In addition, there are a number of other read-through agents currently being evaluated for potential in vitro and in vivo use. An inborn error of metabolism like TMAU would be an excellent candidate for this type of therapy, as an increase of enzyme activity to perhaps as little as 10% of normal should be enough to overcome the biochemical block.


Get new posts by email

15 March 2018

Sulfide and Methane production in humans : FBO connection ?

This is a very speculative post.
It is said that in the HUMAN MICROBIOME, that people tend to be either :
Sulfate reducers (so, sulfide producers)
or
Methane producers

It's not clear how much is known about the microbiome but the word seems to be the population is split 50/50 being either dominant in Methane or Sulfide producer.

It would be interesting to see if those who identify with FECAL BODY ODOR and the spectrum including fart, raw cabbage etc tend to be in the SULFATE REDUCER group.
Nothing has shown up in Ubiome results yet, or at least what I have seen.

Methane in humans would tend to be produced by Archaea microbes, which funnily have been suggested as a potential TMAU therapy (they would break down TMA).

Sulfide producers would probably be mostly due to DESULFIBRIVIO bacteria, but possibly other sources.

It seems odd that in 2018 humanity still doesn't seem to have documented what cause stool smells exactly. Good guesses can be made but there seems to be no consensus and few papers.   


Get new posts by email

6 March 2018

Holistic Therapist asked about candida and FBO


Holistic Therapist asked by a viewer if candida may cause his FECAL BODY ODOR

I don't agree much with the conclusions of this Holistic Therapist, but it's good to see 'Fecal Body Odor' getting a bit of publicity.

Fecal Body Odor is the term most of us identify with in practice. In truth I think it's worse than that, with a spectrum of sulfides not just limited to feces. So it could range from :
rotten eggs,
boiled cabbage,
flatulence,
dog doo,
feces
...
all depending which sulfides are most abundant at any time.

Candida dysbiosis :
When people talk of candida they mean CANDIDA OVERGROWTH IN THE GUT.
It does not mean candida in your bloodstream, which would mean you are near death, maybe have final stage aids or pneumonia in your 90's. It means your immune system is whacked.
So we mean candida overgrowth in the gut.

Do I think candida overgrowth could cause 'fecal body odor'  ?
I do suspect it could be part of the 'syndrome'.
BUT ... 99.99% of people with candida overgrowth do not have 'fecal body odor'.
So I think FBO is often a SYNDROME, with the main factor being sub-par FMO3.

FMO3 Theory (by me) :
SUB PAR FMO3 -- means prone to gut dysbiosis -- bigger sulfide loads

What type of dysbiosis in FBO ?
I don't know.
Some thoughts :
just general dysbiosis, possibly mainly candida
a particular 'FBO' dysbiosis,

FMO3 function %
I think most people are probably around the 80%-100% FMO3 function range, with their enzyme fluctuating due to pressure from genetic weakness.
This makes most people 'mild' genetic cases and probably TRANSIENT cases.

In summary :
I think people with FBO often have gut dysbiosis as part of the syndrome, but the main factor is sub-par FMO3 function. But getting rid of the dysbiosis may be enough.
Candida is a good candidate as the main dysbiosis cause, but it could be other things.

The above is speculation by me. 


Get new posts by email

14 January 2018

the 'big 3' FMO3 variants : a cheap way to test

There are 3 common variants for FMO3, that perhaps most 'FMO3 smell people' carry. The easiest and cheapest way to find out is to do the 23andme.com test, or an ancestry test that lets you download the raw data.

FMO3 is a 532 amino acid sequence, and 23andme only test about 50 of the 532, but it does test the 3 main variants at codons 158, 257, 308.
It would be interesting to see if most of carry 2 or more of these.

Estimates of carriers of the 3 main variants :
E158K : 40% people ?
E308G : 20% ?
V257M : 10% ?

DIY STUDY
We should be aiming to flood PUBMED with papers about TMAU, SysBO/Hali etc.
PUBMED is where researchers look to see whats going on.

But for now, as beggars, we can try a DIY STUDY.

Question 
Do you carry E158K, V257M and/or E308G ?

Feel free to put your result in the COMMENT SECTION.
Anon if you want ?
e.g.
E158K : AG
V257M : AA
E308G : AG

HOW CAN I TEST FOR THIS ?
A cheap and easy way to test for the 3 most common FMO3 variants is :

1. Find and buy an ancestry test that lets you download the RAW DATA ...
or buy 23andme.com test.

2. Look for these 3 variants :


rs2266782
variant known as E158K
normal : GG
variant : A

rs1736557
variant known as V257M
normal : GG
variant : A

rs2266780
variant known as E308G
normal : AA
variant : G


FMO3 PROTEIN is a 532 amino acid sequence, but there are 3 most common variants. E158K V257M E308G . Many people carry these faults (Whites carry maximum for the 3 : 45%, 25% 10% ...  estimate from memory). No-one is bothered much to find out if they are 'pathogenic' or not, but it would be interesting to see if those who identify with metabolic malodor tend to carry them in a mix.

My own current view :
I suspect most cases of 'metabolic/systemic body odor' are due to weakness in the FMO3 enzyme, but there may be other enzyme disorders too.

COMMENT SECTION
Feel free to put your result in the comment section. Anon if you want.


Get new posts by email

2 January 2018

Wevers & New Halitosis disorder : DMS and CH3SH

A new paper by Drs Wevers, Winkelman, Tanger et al, puts forward the theory that there is a newly discovered disorder that can cause metabolic/systemic halitosis.

The volatiles that cause the smells : DIMETHYLSULFIDE and METHANETHIOL .
Enzyme at fault : SELENBP1 .

title : Mutations in SELENBP1, encoding a novel human methanethiol oxidase, cause extraoral halitosis
Pubmed Abstract :  link
Full paper : Link

First impressions of this new paper/discovery :

1. IMHO it could be classed as the MOST IMPORTANT METABOLIC BODY ODOR DISCOVERY SINCE THE 'DISCOVERY' OF TMAU IN 1970.
The reason being that the concept of 'metabolic/systemic body odor' has relied on 1 compound (Trimethylamine) to prove the concept and be the 'sole' disorder, so more compounds to the list are welcome.
In a perfect world society would say 'let's now find all the metbo compounds' ... but society is not interested.

2. They feel that the gene to blame is SELENBP1 for this new disorder.
I still suspect FMO3 is to blame, so I will keep an open mind for now.

3. DMS and CH3SH are the compounds to blame for this disorder.
People with 'fecal body odor' (as it's known) complain of smelling of many nasty smells. To me, DMS and CH3SH are far better suspects for causing FBO rather than TMA, and they are probably in my top 5 list of potential FBO smell suspects, so to see them identified is very welcome.
I suspect there may be a few more (probably mostly Volatile Sulfur Compounds, thiols') suspects to add to the list, but I regard these 2 as potentially 'main players'.

My example list of FBO suspects (guesses):
Probably VSCs or Thiols ... e.g.

DMS
Methanethiol
Dimethyldisulfide
H2S
Cysteamine (?)
Way down the list .... TMA

When someone has metabolic BO, the 2 questions are :
1. What compounds are causing the smell ?
2. What enzyme(s) are supposed to neutralize those compounds.

So in this case I think they have identified bigger 'players' of the group of compounds that cause FBO, but wrong enzyme (could be wrong).


The 'urine' test for the new 'metbo disorder' : High Dimethylsulfoxide.
For the urine test they go for DMSO level.
Perhaps DMS and CH3SH are too volatile to rely on in a urine test, and may already have dissipated or altered. They seem to go for the OXIDE of DMS, which is perhaps the natural end product, and judge it on higher levels.
I would suggest this is definitely a test we should take.

About Wevers, Tangerman, Winkel et al :
The paper included the 3 above Drs, as well as many others. They have known to have a long interest in the causes of Halitosis, including metabolic causes.
That said, this paper may have taken 10 years (or more) to publish, so my 2 thoughts on their research are :
1. Whilst I welcome it, I am not relying on any breakthrough in society and Drs knowledge of met BO/hali in the near future.
2. I'm hoping perhaps they have 'stored' research and will announce treatments, test options, as a quickfire bundle of announcements this year, but I'm doubtful.

So in conclusion, my current view is :
Potentially 'top of the list' compounds identified to cause metbo body odor.
For now, I'm still a 'FMO3ist' rather than thinking it is SELENBP1.

Them :
compounds : DMS and CH3SH.
enzyme : SELENBP1

Me :
compounds : DMS and CH3SH (and a few more VSCs, thiols etc).
enzyme : FMO3   

Other potential metbo disorders :
I write mostly about my opinion as to the cause of FBO, which seems the main complaint.
I am sure there will be other metbo disorders, but these will be limited to perhaps 1 compound (or a small family), and to other genes.
FBO seems a wide spectrum of smells, so IMHO is most likely a 'broad spectrum' gene, whereas other metbo genes will have a  one distinctive smell (probably), such as isovaleric acid.   

What compounds make feces smell ?
Everyone knows the smell of poo can vary, so for the most part it seems that the compounds that make the smells are varying too. A guess would be they are mostly VSCs / Thiols, and a few other compound families thrown in. But for the most part they would seem to be sulfur compounds.
It may be a surprise to know the World Scientists do not yet have a definitive list of the compounds that make poo smell. Occasionally a researcher (such as Levitt et al) will do a few papers, but many might disagree with them.   

Media links to the story
Gizmodo
Medical Xpress
Science Daily
Genengnews
UCLA press release

Dr Wevers webpage


Get new posts by email

2 October 2017

Ulcerative Colitis and phosphatidylcholine (and FBO)

There's a theory going around that PHOSPHATIDYLCHOLINE (PPC) may be a therapy for Ulcerative Colitis.
It seems that PPC plays an important role in protecting the intestine lining.

Why would this be of interest for Systemic Body Odor ?

1. A lot of people with 'fecal body odor' / TMAU report of suspecting they have  LEAKY GUT (where the gut lining is not acting as a fine sieve as it should, instead the sieve having holes and letting through bigger things to the bloodstream). 
Whether there is a connection between 'leaky gut' and 'FBO' is not known, though it seems very possible.
However, it seems most people with leaky gut do not have FBO (i.e. FBO people will be a small % of total leaky gut people),
so perhaps it is part of a FBO syndrome symptom for people prone to FBO (i.e. probably a FMO3 fault being the main reason for ending up in the syndrome).

2. PPC is a form of choline.
A speculation is that TMAU-prone people are naturally deficient in choline. 

The 2 scenarios would be :
1 eats lots of choline ... choline is altered to tma by gut microbes ....
result : lack of choline for the gut lining and for the bloodstream.
2 diagnosed and avoids choline .... not enough choline.

How much consensus does the Ulcer Colitis - PPC theory have ?
There's not many papers on it, and it seems it may be just one of those theories that has been suggested but not made it to mainstream. So in effect nobody knows.


Links of interest about the theory

Nestle have patented a PPC product in 2016 
(the big pharmas patenting 'natural' things is often a sign where the advertising for the industry will go) : Nestle PPC product.
note : when pharmas patent a natural product, they seem to have to do something to it to make it not just the natural product ... i.e. bundle it with a combo of things to make it 'unique'. 

Dr Myhill has mentioned the UC-PPC theory on her site.
Dr Myhill link
Dr Myhill is an open-minded UK GP who the GMC tried to strike off. She is aware of gut candidiasis, leaky gut etc.

Random pubmed paper on the UC-PPC theory : link

Final comment
It's interesting a theoretical connection to UC-PPC has been made, and perhaps there is a connection for FBO people too.
But for now, we don't know but can follow up.

Acronyms :
FBO : Fecal Body Odor
UC : Ulcerative Colitis
PPC : Phosphatidylcholine

Reason for posting (FBO connection) :
If people with FBO tend to have 'leaky gut', perhaps it's due to the gut microbes eating the choline and creating a lack of PPC for the gut lining (probably mostly the colon).
Example : gut microbes in the small intestine ... get first go at diet choline ... lack of PPC reaches the colon. 

Best ways to get PPC :
1. Pure(?) PPC (expensive).
2. Lecithin. About 1/3 PPC ? But also contains normal choline ?

Get new posts by email

3 September 2017

Mice on high choline diet deficient in choline : Paper

This could be a very important paper for the following malodor problems :
TMAU (if you believe that TMA is the sole source of your malodor).
Possibly 'FMO3 malodors' (if you think many FMO3 substrates cause your smells).
Possibly (in theory), if low blood choline caused smells (this is an unknown).

2017 Paper :
Metabolic, Epigenetic, and Transgenerational Effects of Gut Bacterial Choline Consumption
Romano KA et al
Unis of Wisconsin and Harvard

in the news : link


Summary
Choline is an essential nutrient and methyl donor required for epigenetic regulation. Here, we assessed the impact of gut microbial choline metabolism on bacterial fitness and host biology by engineering a microbial community that lacks a single choline-utilizing enzyme. Our results indicate that choline-utilizing bacteria compete with the host for this nutrient, significantly impacting plasma and hepatic levels of methyl-donor metabolites and recapitulating biochemical signatures of choline deficiency. Mice harboring high levels of choline-consuming bacteria showed increased susceptibility to metabolic disease in the context of a high-fat diet. Furthermore, bacterially induced reduction of methyl-donor availability influenced global DNA methylation patterns in both adult mice and their offspring and engendered behavioral alterations. Our results reveal an underappreciated effect of bacterial choline metabolism on host metabolism, epigenetics, and behavior. This work suggests that interpersonal differences in microbial metabolism should be considered when determining optimal nutrient intake requirements.
in the news : link

My interp
It seems they wanted to see how mice differed between groups that had 1:abundant bacteria that turn choline into TMA ... and 2: mice that had a cloned enzyme that blocked microbes changing choline into TMA.

The results were
The TMA-microbe rich mice had low choline blood levels even on a normal choline rich diet.
This is because the gut microbes COMPETE with the host for choline (and microbes get first go).
This caused significantly lower METHYL DONOR metabolite levels in blood and liver, as choline is one of our main methyl donors.
The low blood methyl/choline levels in blood seemed to cause behavioral problems (e.g. anxiety).

Choline
Seems to be one of our main METHYL DONORS (in the blood).
Is an important fat decongestant for the liver.
As we can make some, it was regarded a non-essential nutrient, but now it is accepted that we cannot make anywhere near the amount we need, so is in effect an essential nutrient.

Behavior problems
It's interesting they report the 'low choline blood' mice as having behavior issues such as anxiety, as many with TMAU report of anxiety.

My thoughts
I have thought this before, that low choline blood may be an issue for anyone with 'TMAU' who eats a high choline diet, or even worse for someone following a low choline diet.
As said, choline is important for the liver and as a methyl donor.

NAFLD
I do wonder if perhaps those with TMAU are prone to non-alcoholic fatty liver disease. Perhaps in general or in a particular way. Very speculative.
Many Drs feel that most westerners will have some fatty liver say over 40+, due to diet and lifestyle. But perhaps low choline could be an issue.

Appropriate tests :
1. I guess a liver ultrasound to see how the liver is. (mainstream test)
2. Choline blood test. This is not mainstream and seems very hard to find. It should be mainstream but it's not.

What can a TMAU person do to raise choline blood levels ?
It would seem impossible as the choline will be altered to TMA before it is absorbed.
One choline expert suggested phosphatidylcholine was less easy for microbes to alter, and may be worth a try (unlikely ??).
My own view is that testing for choline blood level would be the best option, so we could see if there was a 'syndrome' common to us.

TMAU low choline predicament (my theory)
2 scenarios
1. High  choline diet (normal west diet) > TMA microbes eat the choline before they are absorbed > person has low blood choline.
2. Person goes on low choline diet > even lower in blood choline level.

They cloned an enzyme in the microbes that did not produce TMA
I note they mention they had an enzyme cloned and put into microbes that stopped production of TMA.
My guess is this approach would be an obvious therapy for TMAU.
Something we should certainly investigate.
My opinion : PROBIOTIC THERAPY with CLONED MICROBES that don't carry CHOLINE-TMA enzyme is one of our best hopes.

Could low choline blood levels cause the smells ?
I guess it's possible that LOW CHOLINE BLOOD levels could cause the smells for metabolic/systemic malodors to do with related enzymes (e.g. FMO3) , but for now it must be deemed an outside chance but definitely one worth following up.

My advice for now 
Try and find a test supplier to do the choline blood test (possibly very difficult).
And perhaps a liver ultrasound to see if you have some fatty liver.

 Get new posts by email

20 March 2017

Idea : TMAU Awareness week ... every 6 months

notion of a TMAU AWARENESS WEEK every 6 months.

Most disorders have a yearly awareness week. TMAU would do well to have such a week, as it is possibly the most 'unknown' documented 'rare' disorder (I don't think it is rare. Severe TMAU1 may be, but transient cases might be 1%+ imho).

But why wait yearly ?
If you live to 80 you will see only 80 'rare disease' days.
In many countries political parties now have twice yearly conferences. This will be due to party member pressure, feeling yearly too long a gap, and they are right. A year is a long time for causes.

So it would be great if the TMAU community could arrange :
TMAU AWARENESS WEEK (every 6 months)
(in my opinion)

What would it involve ?
An ad campaign (funded by specific crowdfund campaigns).
Maybe lobbying politicians or getting a patron politician involved.
Perhaps test labs releasing latest test result stats.
Maybe someday a conference (like the 1999, 2002 conferences which were meant to be bi-annual, 2001 moved due to 9/11)

An example of a disorder awareness week (UK Downs Syndrome)


Get new posts by email

1 March 2017

New paper : TMAU might not just be FMO3 disorder

New TMAU paper by Monell et al.
Conclusion (?) : TMAU might not just be because of FMO3 enzyme.
Paper funded by NORD grant crowdfunded by TMAU community in 2011.

Around 2009-2011 a TMAU community group spearheaded a crowdfunding campaign to get the NORD TMAU grant past it's $25K trigger point so that researchers could put forward proposals for the grant. The grant was awarded in 2011 to a Monell Chemical Senses proposal. This month the paper has been published in a peer journal.

NORD grant TMAU paper : Genetic analysis of impaired trimethylamine metabolism using whole exome sequencing

Conclusions
Thus, variants in genes other than FMO3 may cause TMAU and the genetic variants identified here serve as a starting point for future studies of impaired TMA metabolism.

My interp of the paper 

My interp is they are saying genetic TMAU may not just be just to FMO3 enzyme flaws. In particualr they mention PYROXD2 enzyme, which has been mentioned in TMAU circles before (can't recall why).  

My own view on the paper (bad analogy ... suspects and safehouses)
If you think of 'volatiles' as the suspects, and FMO3 as the safe-house, they are saying the suspect (TMA) stays at various safehouses, TMA is to blame for all the smells, and only TMA should be followed about even when it leaves FMO3 'house' to other safehouses.

My own current view is the only safehouse to watch is FMO3, and note all the 'volatiles' that stay there. In fact I reckon TMA is a 'small player' and other FMO3 'safehouse' suspects are more likley to blame for smells. Probably the likes of dimethylsulfide.

So this new paper has went in a direction that doesn't fit with my current thinking, but it is 'new' in that they are suggesting TMA might be metabolized by enzymes other than FMO3 (?).

Paper view
Current Safehouse : FMO3
Suspect : TMA is only suspect.
Paper : TMA might have other safehouses.

My View
Safehouse : FMO3
Suspect : many. TMA a small player
My view : No need to follow TMA. FMO3 is only safehouse that matters, Keep an eye on the all suspects at FMO3 house.

Overall, I think so little research has gone into FMO3 and TMA that we may be at 'chapter 1' of understanding them. As this was a small one-off study, I don't expect much more 'TMAU' research on it. But since TMA has been suggested as having a connection with cardiovascular disease, perhaps TMAU people will be able to read on such research from this aspect in future.

Other comments on the paper :

None of the 10 people seem to report fishy smell. Most report 'sulfury'/fecal smells
My impression is that Monell feel TMA causes a fishy smell, but through influence have broadened this to saying TMA might cause smells more broader than that. Personally I think the smells are not due to TMA, but to other volatiles (e.g. sulfides), and in a way TMA is probably a 'small player' but a good biomarker of FMO3 function (? not even sure about that).    

Only one has FMO3 mutations that would be regarded by clinicians as TMAU1 
In academia and the clinical world, the teaching is that genetic TMAU is caused by serious FMO3 mutations. But in this paper only one has taught 'serious' mutations (at codon 148). Or at least, I think faults at 148 are bad. I note that they are not the worst TMAU result in the paper (at about 56%).

All the other FMO3 faults listed are carriers of common 'benign' FMO3 faults

Common FMO3 variants carried by whites by %  :
codon 158 : 20-50% ?
codon 308 -  up to 20% ?
codon 257 -  up to 15% ?

As can be seen, many people carry common FMO3 variants. Currently they are taught as being 'benign'. But in the paper, of the 10 tested, many of them only carry one of these FMO3 faults (mainly 158). Obviously 50% of whites don't have metabolic smells, so it's still an unknown full picture to understand.

The worst TMAU urine result seemed to only carry a PYROXD2 DNA fault.
In this paper, the worst result was #52 who only carried a fault in PYROXD2 enzyme.

Worst result in paper : #52 ... TMAO% output 13% ... FMO3 faults : none ... PYROXD2 faults : carries one

The worst TMAU result had no FMO3 faults and only carried 1 PYROXD2 fault. This throws up more questions than answers. 5 carried PYROXD2 faults (3 were homozygous, 2 heterozygous).

PYROXD2 faults listed : Not in coding part of PYROXD2
To make a PYROXD2 protein, you need an amino acid code. These are the codons on the exons.
Genes also have introns, which are generally regarded as 'junk' or unknown.
In this paper, the PYROXD2 faults listed are in the intronic region (not the exons). So they are not even in the coding part of the enzyme gene.

example of how gene makes a protein.
FMO3 has 532 amino acid code to make the FMO3 protein
this means 532 codons.
Genes also have intron part.
Introns not needed to form the protein, but faults there seem to be able to disable the protein.

PYROXD2 
This enzyme has been listed before in one TMAU paper. I can't recall at the moment.

Final thoughts 
The paper is certainly interesting in that it raises questions about current TMAU  teaching. How much impact it will have ... possibly not much due to lack on interest in TMAU.

I will be looking around at PYROXD2 again in a mild way. My mind is currently too set on FMO3 and all it's sulfide/amine volatiles, rather than TMA.

I have no expertise and my interp and thoughts could be wildly wrong.
My impression is Monell can be sensitive about opinions.

My own current theory on systemic body odor/halitosis
Most people identify with 'fecal body odor'. I think this is due to sulfides, maybe some amines. I think it is due to problems with the FMO3 enzyme. Probably often a combo of FMO3 slight weakness and 'FMO3 substrate gut dysbiosis'.

Get new posts by email

12 February 2017

Youtube : Young lady talks TMAU & Fecal Body Odor


Saying it like it is.
Note about the video :
This is an embed of the original, not a copy.
If this original is deleted or 'sharing' is disabled, it will auto-delete here too.

Comment
Most people report of metabolic fecal/fart smells.
Currently trimethylamine is the only metabolite tested, so the only metabolite test on offer.
People with systemic malodors identify with the TMAU concept, but not the 'smell'.
There still seems a lot to discover about the 'systemic/metabolic malodor' syndrome.
Personally I think for most cases they have identified the correct enzyme but have limited it to one metabolite that may be a 'small player'.  

Get new posts by email

19 January 2017

REACT TMAU Fund : spare a $5 ?

RE(ACT) rare disease site.
Meant for research crowdfunding.
Part of the BLACKSWAN charity.
Based in Switzerland.
Founded by pediatrician Dr Olivier Menzel.

Idea behind RE(ACT)
Rare disease groups can use it as a crowdfund site for research into their disease.
Researchers are supposed to put forward research proposals.
REACT has a expert committee who accept/reject proposals.
If no proposal is ongoing, the money goes in to a fund awaiting proposals.

RE(ACT) TMAU Fund
Throw them $5 ? (or EU/£ )
Problems with REACT
Staff seem to be not around.
Seems to be no users around.
Seems to be only one research fund ever raised of all the disorders.
Generally it seems neglected.
Yet they seem to do annual conferences.

REACT TMAU FUND : throw a $5 their way ?
Maybe if you have a spare 5 $/£/EU you could donate it to the TMAU Fund as a wake-up call.
Consider it money wasted.

Good things about REACT TMAU FUND
You can see the amount raised on their site.
Money does seem to at least stay in the fund (possibly forever).
Does not seem to get transferred into a general fund if deemed redundant.

SYSTEMIC MALODOR/TMAU community should have their research fund(s)
examples, Research Fund(s), campaigns such as awareness campaigns (e.g. Bus ad, conference) ).
Main ideas :
Needs to be transparent.
Needs to have broad support.  
Needs to be trusted etc.

Crowdfund campaigns etc
Examples : Individuals or small groups could start TMAU/Malodor crowdfunds.


Get new posts by email

30 December 2016

Putting FMO3 through the 'drug repurpose' checklist

FMO3 has been taught that it cannot be induced as most other redox enzymes can (e.g. the CYPs).
Perhaps this thinking is because so few have investigated FMO3.
A recent paper suggested a Korean herbal mushroom may induce FMO3.

DRUG REPURPOSING :
A (new ?) method of (relatively) 'inexpensive' enzyme research is to check how drugs past their patent period to see if they may be of any use in other health conditions.

Drug Repurposing for enzyme disorders (e.g. FMO3)
For enzyme disorders this probably involves checking the reaction of  the enzyme to a list of unpatented drugs in a lab (e..g FMO3). In this case a priority would probably to be to see if it can INDUCE FMO3 (i.e. make it work harder) so you maybe get another 10-20% output.

Main benefits of Drug Repurposing (?) :
It's RELATIVELY inexpensive.
It should be reasonably quick and easy to do (? a year ?)
A lot will be known of the drugs already.  
May learn more about enzyme (e.g. a group of compounds induce/inhibit)

RESEARCHER INTERESTED IN FMO3 DRUG REPURPOSING
A researcher has shown an interest in putting FMO3 through the 'drug repurposing' check.
As usual funding would be the issue.
A opening estimate is that it may cost around $US 74,000 (probably mostly to hire someone to run the checks.)
An opening estimate is that it would take around a year.
They are looking at possible ways of getting funding but it's difficult.

It's something the community can think about.

Links about Drug Repurposing :
NIH USA website
wikipedia
101 website
findacure UK 

FMO3 and Systemic Malodor
My own interest in FMO3 is because I currently suspect it is my main suspect enzyme for most cases of 'systemic/metabolic malodor' (i.e. caused by an enzyme deficiency or overload, not hygiene etc).
FMO3 oxidizes many sulfides and amines in humans. But other enzymes cannot be ruled out.

Current possible therapies for TMAU or FMO3 'smells' :
TMA inhibition/reduction in the gut (e.g. Cleveleand Clinic working on a reducer to be marketed as a supplement by P&G. Not known when it will be available).
TMA metabolization in the gut (e.g. 'probiotic' that metabolizes TMA. Probably a 'methanogen' which will take it the methane route.)
'Gene Therapy' (probably ideal option)

Get new posts by email

11 December 2016

AIRE Breath Sensor for FODMAP

Foodsniffer (not the AIRE)
A start-up called FOODMARBLE is launching a breath sensor.
Called the AIRE Breath Sensor.
It is designed for the FODMAP diet.
Detects : HYDROGEN levels ?
Hydrogen is thought to be the main gas given off during gut fermentation.
Hydrogen is used as the gas tested for 'small intestine bacterial overgrowth'.

Possible interest to those with systemic body odor/halitosis :
The blog current view is that FMO3 enzyme may be the weakness for most type of SYSTEMIC BODY ODOR (SBO).
Many of the gases from gut fermentation are probably FMO3 substrates (e.g. certain sulfides/amines).
Many with 'fecal body odor' feel they have 'gut dysbiosis'.
Something like the AIRE may help them track their 'dysbiosis' via hydrogen level.


Initial thoughts about the AIRE :
It's version 1. With hindsight it may be regarded as not very good.
BUT, people with SBO will for the foreseeable future need 'sensors' (probably breath sensors).
If it worked, it may be of some use to track 'gut dysbiosis'.
The platform (device for phone, bluetooth etc) is ideal for the consumer. A SBO sensor will be probably the same (but detect different gases e.g. dimethylsulfide).
Great price ($99 intro price). At that price it's worth a gamble.
(note : I already bought the 'foodsniffer' and 'mint breathometer' (not arrived after 2 months), so will probably not be buying the AIRE soon).

AIRE Sensor website
Twitter
Daily Mail (dec 16)
Press Release (dec 16)
Business Insider (may 16)

Systemic Body Odor needs a Consumer Sensor :
SBO will need it's own version(s) of a 'sensor'. Once it's known what gases act as biomarkers or to detect all the types of gases that cause SBO. A good 'suspect' would be 'dimethylsulfide'.
Currently such a sensor does not exist for systemic body odor.
Partly as the technology had not reached a decent level yet.
Also it seems sensor makers are only realising there was a consumer market for say 'halitosis' sensors, or hydrogen sensors. More because of start-ups getting in the market via crowdfunding.
with SBO, the person usually cannot smell themselves (my opinion, they are usually transient and the brain ignores it's own circulating smells).

One thing is for sure, SBO will need a sensor that detects SBO gases.
Currently we do not know what these gases are (apart from trimethylamine).
It's likely sulfides like dimethylsulfide will be suspects.

Fecal Body Odor :
Probably it's unknown exactly what gases make fecal smells.
Scientists will have a good idea of suspects, but papers are few and contradictory.
Perhaps for SBO, there may be a wide spectrum of sulfides/amines at any point, but perhaps a handful of 'big players' (e.g. dimethylsulfide) which could then act as 'biomarkers' for a sensor.

Possible 'big players' for Fecal Body Odor (guesses) : 
dimethylsulfide
dimethyldisulfide
methanethiol
cysteamine

FINAL THOUGHTS
The SBO community will need their own 'sensor' as they are 'nose blind' to their own smells.
The tech (and makers will) has not been there for consumer sensors.
But over the last 2 years, both the tech and now we see the will, for consumer sensors is happening.
No sensor maker would currently probably invest in a 'SBO sensor', thinking there is no market.
But other sensors may longterm make the process cheaper.
Many with SBO feel they have 'gut dysbiosis', so a sensor like the AIRE may be worth a gamble.
Keep in mind for AIRE it's version 1 (i.e. early days).  

What SBO needs
1. To find out all (or at least the main) volatiles that cause SBO (exploratory tests).
2. From that info, a diagnostic test.
3. A Sensor(s)
4. A DNA test (probably being superceded by exome/genome tests which are mathing price of single gene tests).
5. Therapies/cures.


Get new posts by email

15 November 2016

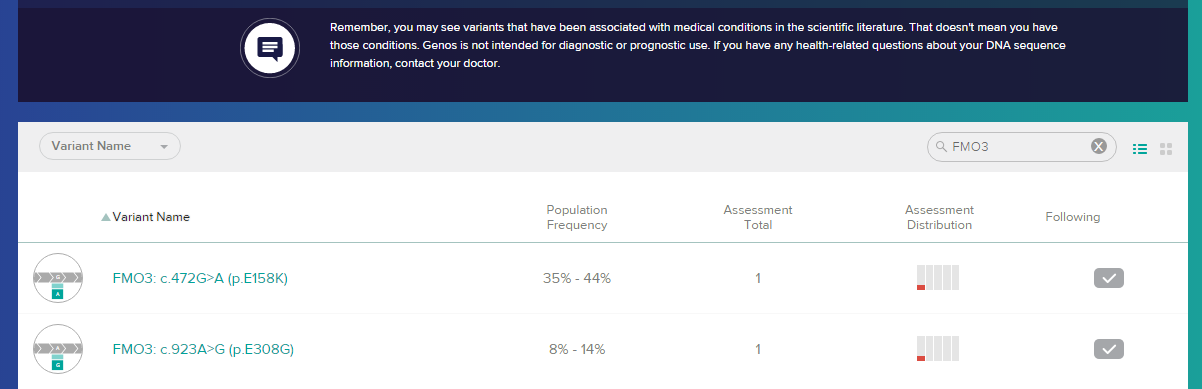
FMO3 gene results with GENOS

I got my Exome test results back from Genos (DNA test).
Cost was $399 (time limited special offer).
Exome is coding part of the Genome (essential part).
For FMO3 the test listed my 2 'wrong amino acid' variants, but not the 'silent' one.
I can't be sure it is FULL SEQUENCING, but rather a 'list of suspects'.
Overall I think it was worth it.
Best overall DNA tester I know (being both for consumer and none of the obstacles of clinical labs).

I got my exome DNA results back from GENOS.
I am very happy with the service, the process, support, and the info given.
My only gripe is I am not sure if it is FULL SEQUENCING (i.e. every codon of a gene).
It possibly is, I don't know yet.

Ways DNA labs test and give results :

1. Test for list of suspect variants/codons only (usually cheapest way).
This is no use really. Still too much unknown of the other bits. This is where they test suspect codons only. This means they choose the list of known suspects, but many more variants may yet to be discovered as fault-causing. You want to know every variant you have, not just suspects.

2. FULL SEQUENCING, but only give SELECTED variants/codons info to the person.
This means they tested every codon but they may only give what they think is relevant info on certain variants. So you still can't be sure you are getting the whole picture.  

3. FULL SEQUENCING and give ALL VARIANTS whether they be thought relevant or not.
This would be as good as FULL SEQUENCING in theory I guess.

4. FULL SEQUENCING (i.e. every codon of the gene)
This is best/good, though I guess in theory you only need to know the variants, so #3 may be more practical. #3 is the same as #4 but without the 'perfect' parts (which presumably won't affect function).

I am hoping Genos is #3, but I have not found out yet. It may be #2 which would not be so good.

EXOME, GENOME :
Exome  = coding for all the proteins in humans
Genome = everything (Exome + Junk + promoter regions etc)

It's thought maybe 80% of faults are in the exome part.
The main reason for EXOME testing rather than GENOME is cost (at the moment).
Exome is obviously the part you can't do without. The essential part.
But people can have faults in the junk part of a gene and it can cause deficiency even though it's junk.
   
MY GENOS DNA RESULT
I have fully sequenced the FMO3 gene before so knew my FMO3 coding part result.
It spotted my 2 carrier copies of the common variants at codon 158 and 308.
These are reasonably common (in caucasians anyway).
There is debate if they affect function (obviously I would say they do).
Some say only if they were from same parent, or if person is homozygous (carry 2 copies).

It didn't spot a silent variant I carry. This is what makes me wonder if they only test a 'suspect list'.
Silent variants are where one of the nucleotides is wrong but the amino acid ends up the same.

FMO3 gene
532 x 3 (1596) nucleotide sequence.
makes up 532 amino acid sequence (+ stop at 533).
makes up the FMO3 protein.
Which means 532 codons where variants can be.

Clinvar list of FMO3 variants

IS IT A GOOD WAY TO DNA TEST FOR FMO3?
Well this is where I don't know (yet).
The best way is to have your full 532 coding sequence, or at least all the variants in that 532 coding sequence (even if they are currently deemed to not matter).
But I don't seem to have the full sequence (not that I can see so far), or all the variants (as they missed a silent one).
The give a raw file but I don't know how to open it.
Answer : I think so but I don't know.

FMO3 DATABASE
In my opinion we should get a FMO3 database going.
But how to, I don't know.
Ideally this would be both the Exon and Intron parts of FMO3 (not just the exons)
Intron is the 'non-coding' part of the gene (which could be junk + promoter region etc).
This would be a pipe dream.

My philosophy on spending on 'systemic malodors'
My philosophy is we don't know what causes it yet, so better to spend money on testing rather than spending on supplements.

FINAL COMMENT
So I can't say for sure GENOS is a great option for DNA testing, but it may be.
And at current price $399 it's cheaper than most FMO3 DNA gene testing .
Plus it's meant for the public and easy to test (saliva).
The question is how much prices will drop quickly and how well competitors do.
In the end you will probably be able to do GENOME testing for maybe $100, but when ?
Also remember, you may find results of other genes you might not want to know (e.g. prone to parkinsons, carrier of cystic fibrosis) so you need to factor in whether you want to know such things.

Note :
I am no expert, so terminology, facts may be wrong.

Links :
Genos DNA TEST LAB FOR CONSUMER


Get new posts by email

25 October 2016

Bacteroidetes don't produce trimethylamine from choline

 2012 paper suggests bacteroidetes phyla are poor at degrading choline to trimethylamine.
Firmicutes, Actinobacteria, and Proteobacteria can produce TMA.
Ubiome suggest Firmicutes make up 60% of normal flora, Bacteroidetes 30%.
My own Ubiome results average (of 4) were Firmicutes 70%, Bacteroidetes 26%.
My own opinion, not enough known of the gut flora for me to have an opinion.
This post more a 'for your information' post, rather than any 'breakthrough'.
Perhaps others should try stool DNA testing.

The new Phillips/Shephard TMAU-FMO3 overview paper mentioned a 2012 paper which they seemed to have great credence for. The research in the paper proved TMA could be produced from choline by certain gut bacteria flora phyla (Firmicutes, Actinobacteria, and Proteobacteria) but not from Bacteroidetes.

Quote from Phillips/Shephard/Fennema paper

Free choline is absorbed throughout the small intestine and is subsequently integrated into cell membranes or actively taken up by the liver, where it can be converted to betaine, phosphocholine, or lecithin (Zeisel, 1990). High amounts of choline may exceed the absorptive capacity and pass through to the large intestine, however, where it is metabolized to methylamines by microbial action (Zeisel et al., 1983). Choline is a quaternary ammonium compound containing a trimethylammonium moiety. Thus, it can act as a precursor for TMA (Zeisel et al., 1989; Chalmers et al., 2006). The bacterial conversion of choline to TMA involves the cleavage of the carbon-nitrogen bond of choline, producing TMA and acetaldehyde (Hayward and Stadtman, 1959). Craciun and Balskus (2012) proposed that a glycyl radical enzyme CutC (EC 4.3.99.4), encoded by the bacterial choline utilization gene cluster (cut), might act as a choline TMA-lyase to catalyze this initial step in choline degradation (Fig. 1). This was confirmed by demonstrating that deletion of cutC in Desulfovibrio desulfuricans abolished the ability of the organism to produce TMA from choline. Bioinformatics analysis revealed cutC homologs in 89 bacterial genomes. The homologs are not distributed evenly among the major bacterial phyla of the human gut, being present in Firmicutes, Actinobacteria, and Proteobacteria spp. but absent from Bacteroidetes (Craciun and Balskus, 2012). Table 1 shows bacteria known to be associated with formation of TMA via choline degradation.

This is the paper they refer to :
Microbial conversion of choline to trimethylamine requires a glycyl radical enzyme

Firmicutes and Bacteroidetes seem to make up the bulk of the gut flora. There seems to be different opinions on what that % make-up should be for a healthy gut.

Ubiome suggest the healthy gut should have about 70% Firmicutes and 30% Bacteroidetes.

My own Firmicute/Bacteroidetes ratio :
I have tested with Ubiome 4 times.
In 3 samples my Firmicute was slightly higher than normal. Bacteroidetes was slightly lower.

My view on the knowledge of the human gut flora :
I would suggest if you compare it to the history of USA, it may be around the year 1620. Perhaps I'm wrong, but my impression is so little is understood of the gut flora (Oct 16). I'm hoping technology has caught up and we will be at around year 1900 in the next few years.

My view on my own results :
I will not be excitedly trying to alter my firmicute/bacteriodetes ratio, though may look around for info. It seems that bacteroidetes are not the type usually put in 'probiotics'. Possibly partly as they are so 'sensitive' (and die easy in oxygen). Possibly there is no 'bacteroidetes' probiotic on the market. The general view seems to be taking 'prebiotics' is the best hope of feeding bacteroidetes.

Perhaps others can do the stool DNA test :
Since the stool  DNA test is relatively cheap, and sometimes they do special offers (e.g. 3 for 1), perhaps others with systemic body odor/halitosis can do the test and mention anything they want about the results in the comment section of this post.

Stool DNA test suppliers :
Ubiome (choose citizen science)
American Gut (also 'UK Gut')

These are the 2 best known suppliers. Thankfully, they are consumer health friendly, and not health learning obstacles as is the case with normal DNA tests, urine tests etc. The spirit of the testing would be that it may be not very useful, but perhaps will be in hindsight.    

What's this to do with systemic body odor ?
My own view is that most cases of SBO are probably due to enzyme weaknesses, probably the bulk of which are due to sub-par FMO3 enzyme function. But I also think gut dysbiosis will be a common factor in 'FMO3 body odor', probably as part of the syndrome, and perhaps often the 'tipping point'.

Currently TMAU is the only acccepted form of systemic body odor. My own view is that 'FMO3 body odor' can mean smelling of any FMO3 substrate rather than just TMA, and many of the volatiles produced in the gut are probably FMO substrates. Although this paper was about TMA, perhaps bacteroidetes can't produce other FMO3 substrates, but who knows.

Get new posts by email

3 September 2016

TMAO and Alzheimers ? (new paper)

New paper.  Since 2011, Trimethylamine-n-oxide has been postulated by a Cleveland Clinic paper as having a connection with atherosclerosis (and so Heart Disease). Before this 2011 paper trimethylamine metabolism in humans was ignored. Since then it has been suggested as possibly having a role in many of the worst health problems in humans.

List of diseases postulated as having a possible connection with TMAO (so far, all since 2011) :
Diabetes.
Chronic kidney disease.  
Atherosclerosis (e.g. heart disease, stroke)

And now, a paper postulates that TMAO may be associated with Alzheimers (Alz) :
Paper : TMAO and Alzheimer's
Xu R, Wang Q
Dpt of Epidemiology and Biostatistics, Institute of Computational Biology, School of Medicine, Case Western Reserve University, Cleveland
ThinTek LLC, Palo Alto


Context of the paper (my view) :
Seems to be a 'computational' look at microbiome stats to look for a connection between gut microbiome compounds (only) and Alz. The conclusion seems to be TMAO could be of interest as a biomarker. 
I have not heard of the authors or labs. 
It should be kept in mind that it seems pretty speculative (for now) and many of these types of papers are put out, often contradicting.
I'm not thinking it's correct or false or significant (yet).
Quote :
We identified common genetic pathways underlying AD biomarkers and its top one ranked metabolite trimethylamine N-oxide (TMAO), a gut microbial metabolite of dietary meat and fat. These coregulated pathways between TMAO-AD may provide insights into the mechanisms of how dietary meat and fat contribute to AD.
What's this to do with systemic body odor ?
Currently the only volatile tested for SBO is trimethylamine (TMA), and the only documented SBO is trimethylaminuria (TMAU). Until 2011 there was no interest in TMA metabolism in humans. Now since the CVD-TMAO theory (and other diseases), TMA metabolism is of great interest. This co-incidence is very good news for those who feel they have TMAU only (i.e. only smell of TMA), as it means great interest in TMA metabolism and will likely lead to 'therapies'. P&G already have a deal with Cleveland Heartlab to produce an over-the-counter 'TMAO-management supplement' (at a guess, a 'TMA-blocker pill'. It is not known when.

My own view :
Currently I suspect that FMO3 enzyme is the right enzyme highlighted as being the main 'SBO enzyme', but that the smells are not limited to TMA. So I am a bit cautious about hoping 'TMA cures' will mean 'SBO cures', but will be buying any TMA therapy by the crate.
I currently have no opinion the 'TMAO connection theory' to diseases, but grateful for all the attention/research to TMA metabolism.


Get new posts by email


31 July 2016

Metabolomic Profiling for Systemic Body Odor

This post is meant to be thought provoking.

Need to discover all volatiles/metabolites that cause systemic body odor.
Once discovered, these volatiles will be known as the biomarkers for the diagnostic test,

Trimethylaminuria (TMAU) was 'discovered' in 1970 by Denver Dr's. A patient's mother had said sometimes their child smelt of fish (they had another serious disorder) and the Drs decided to test the TMA level since they knew this volatile smells of fish.

So the only volatile currently tested for systemic/metabolic body odor came about in an anecdotal case and no-one has looked any further than this since (that's if they even look for TMA). It goes to show how much 'sufferers' need to further the understanding of systemic body odor themselves, as no-one is looking.

Personally I think maybe 1% population could be 'prone' to  transient systemic body odor, probably 'fecal body odor'. Maybe even more. I would guess it may well be the biggest 'undiscovered' metabolic disorder left.

Metabolome Testing
It's only about 18 years since the FMO3 enzyme DNA code was fully documented. So genetics is still at a fairly new stage. Along with genetics, the other science that compliments it is human metabolomics, the study of the metabolites in humans. Again this is a fairly new science, both in knowledge and the technology needed. It does seem to be maturing now.

Metabolomics for understanding systemic body odor
When a disorder is fully understood it will have a 'phenotype' test where they look for the known biomarkers in human fluid to see if the person has the disorder. Since the concept of systemic body odor has not been documented, it will currently need a test like an exploratory metabolome test to look for higher levels of metabolites (probably volatiles). Once they document the biomarkers for systemic body odor, you can then use these biomarkers as the 'disorder test'.

How to do a Metabolome test
First you need to make sure it will look for the 'suspect' metabolites. In the case of SBO, these will probably be sulfide volatiles, but I wouldn't rule anything out for now. I would guess most labs would do a very broad spectrum exploratory test.

examples of 'suspect' volatiles I would look for in systemic body odor :
dimethylsulfide
dimethyldisulfide
methanethiol

Personally I would be looking at FMO3 substrates, as I reckon this enzyme may be to blame for the biggest group of SBO sufferers.

Ease of testing
Since it's a new science, I am unsure of how many labs do metabolomic testing. It's probably not a regular in the mainstream medical health industry (e.g hospitals). Probably more a test done at University labs where trends for testing probably start off.

Also, as usual most labs will probably insist only a Dr can order the test. The usual obstacle to testing used in the medical health industry. Hopefully someday the law will change to allow people to self-pay any test.

Testing Centers :    
Looking around I am not aware of too many potential test centers. A quick google search came up with these possible leads :
Uni of Alberta
Baylor Clinic
Human Metabolome Technologies (Boston)  

The system :
I would say at the moment, expect the system to be against you.


Get new posts by email


re Email sub service : Google is stopping this service JULY 21 new post emails will no longer happen

TMAU Stories

systemic BO/halitosis important links

MEBO Research malodor study 2016

Youtube

FMO3 reference

Blog Archive

TMAU/FMO3 research

Systemic Body Odor links

email :
sysbodyodor@gmail.com

Do you have systemic body odor ?

FMO3 Survey Form

FMO3 DNA test result survey
for those who have FMO3 DNA tested
survey still OPEN

TMA blocker pill (links)

P&G - Cleveland press release aug 2015
1st mention of 'DMB pill' dec 2015
FMO3 DNA testing
Update Aug 17 :
Genos is back with it's EXOME test
link

Note :
Exome/Genome testing may be better option than single gene testing.

See this post : link

Note : Genos Exome Testing.

Exome testing is almost the same price now as single gene testing. Also Genos is consumer friendly, which standard DNA labs are not.

So the blog offer to test solely for FMO3 is almost obsolete, and so no longer offered.


Does Genos fully sequence FMO3 gene ?

At the moment it is not clear, but hoped this will become clear over the next few months

Note : possible 'wild west' way of testing FMO3
Use an ancestry dna site and rummage through the raw data

TMAU Webinar #5 : Preti et al